

Complications that may occur after laparoscopy and ways to prevent them
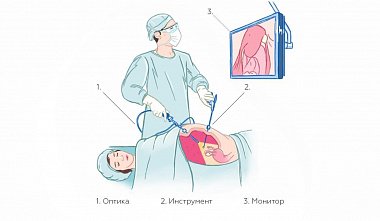
Laparoscopic surgeries can result in both routine surgical complications and complications directly related to the laparoscopic technique and method. These complications can be difficult to distinguish. Some of them are listed below: Organ damage during insertion of the Veress needle or trocars due to "blind" insertion. To avoid this, a number of insertion techniques, tests, and safety-enhancing designs exist. The Veress needle contains a spring-loaded blunt core, the sharp trocar stylets are equipped with protective caps, and there are trocars into which a laparoscope is inserted, allowing tissue observation as it passes through the abdominal wall. However, there is still a risk of damage to the intestine, stomach, liver, and blood vessels. If detected promptly, this complication can usually be treated without consequences for the patient—the organ injury is sutured and bleeding is stopped. Thrombus formation. Risk factors for postoperative thromboembolism include obesity, coronary artery disease, a previous myocardial infarction, hypertension, atrial fibrillation, heart disease, varicose veins of the lower extremities, atherosclerosis, and age over 50. To prevent thromboembolism before surgery, both legs are bandaged from the toes to the groin with elastic bandages in a supine position with the leg elevated. Hemodilators (medications that thin the blood and reduce the risk of thromboembolism) are prescribed, such as fraxiparine, clexane, and heparin. Cardiovascular and respiratory disorders due to the presence of carbon dioxide under pressure in the abdominal cavity. To prevent this complication in the presence of concomitant cardiovascular or respiratory diseases, laparoscopy is performed at extremely low gas pressure. Subcutaneous emphysema (accumulation of carbon dioxide in the subcutaneous tissue of the abdomen, chest, and neck) is quite common, but generally poses no serious threat. The gas dissipates within a few hours or days. Burns to organs and structures during surgery can occur due to instrument defects or a limited field of view. If such a burn goes unnoticed, necrosis and peritonitis can develop. Skin burns around trocars during coagulation sometimes occur. These are usually associated with damage to the insulation of the coagulation instrument, dielectric breakdown, or safety violations when working with electrosurgical instruments. Also, with laparoscopy, there is a higher risk of burns at the site of contact with the "neutral" electrode (the buttock, thigh, or back are selected for its application). This is due to the fact that coagulation is used much more intensively during endoscopic surgery than in open surgery. Trocar wound suppuration may be associated with both general causes (weakened immunity, etc.) and specific procedures, such as removing an infected organ through an incision, such as the appendix or gallbladder. The latter can be prevented by placing the removed organ in a sealed plastic container. However, since such a disposable container costs approximately $100, surgeons in Russia rarely use it. Metastases in the trocar wound area are also associated with removing an organ affected by a tumor through a trocar or a mini-incision. This complication can also be prevented by using various types of sealed plastic evacuators (nets, containers, bags). Despite their high cost, such devices are relatively commonly used in endo-oncology. Bleeding from the trocar wound is associated with insufficient hemostasis during surgery. This complication is rare when trocar wounds are sutured through all layers. In conclusion, I would like to note that the above-mentioned complications are possible, but with proper experience and proper technique, they are quite rare. For example, with qualified endosurgeons, the incidence of all the above complications during laparoscopic cholecystectomy does not exceed 1%.


