

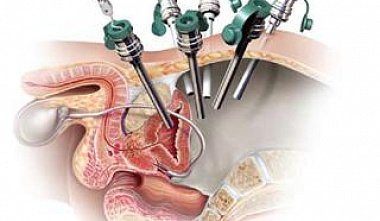
Real-time ultrasound monitoring in laparoscopic radical prostatectomy: impact on positive surgical margin rate
Translation: Sorokin Konstantin Vladimirovich, Head of the Training Laboratory, Russian Cancer Research Center Osamu Ukimura, Cristina Magi-Galluzzi, Inderbir S. Gill Section of Laparoscopic and Robotic Surgery, Glickman Urological Institute, Cleveland, Ohio, USA. J Urol. 2006 Apr;175(4):1304-10. PMID: 16515987 [PubMed - indexed for MEDLINE] This study assessed whether the use of intraoperative real-time transrectal ultrasound (TRUS) during laparoscopic prostatectomy affects the rate of positive surgical margins. The study included 294 patients undergoing laparoscopic radical prostatectomy for clinically diagnosed prostate cancer since March 2001. Patients were retrospectively divided into two groups: Group I (217 patients) operated on without TRUS from March 2001 to February 2003, and Group II (77 patients) operated on after March 2003 with TRUS. The groups were comparable in terms of baseline parameters. By March 2001, the operating surgeon had performed over 50 laparoscopic prostatectomies and was sufficiently proficient in the surgical technique. Black-and-white ultrasound imaging (7.5 MHz) and Doppler scanning were used. Real-time TRUS monitoring was performed before, during, and immediately after surgery. Particular attention was paid to visualizing the vascular and nerve bundles, tracing the contours of the prostate apex, and assessing the location and size of hypoechoic cancerous nodules. Compared with Group I, the positive surgical margin rate for stage pT3 was significantly lower in Group II (57% vs. 18%, p = 0.002). The overall positive surgical margin rate was also lower in Group II (29% vs. 9%, p = 0.0002). Intraoperative TRUS determined the pT2 and pT3 stages in 85% and 86% of patients, respectively. In 54 cases, TRUS visualized hypoechoic foci in the area where cancer was detected during biopsy. Tumor extension beyond the capsule was suspected in 31 cases, resulting in an expanded resection area in these areas to avoid positive surgical margins. Intraoperative transrectal ultrasound (TRUS) has simplified some technical aspects of laparoscopic prostate resection, including: 1) detection of hypoechoic tumor nodes, 2) precise transection of the lateral pedicle and isolation of the neurovascular bundle, 3) reliable extended dissection in areas where tumor prolapse is possible to avoid positive surgical margins, 4) adequate dissection, taking into account the individual structural features of the prostate apex, and 5) separation of the bladder neck, which is difficult for inexperienced surgeons. During surgery, it was possible to monitor the position of the laparoscopic scissors (hyperechoic spot) to ensure safe dissection. Blood flow in the neurovascular bundle was determined before, during, and after surgery. Intraoperative monitoring using TRUS during laparoscopic radical prostatectomy allows for individualized, precise dissection based on the anatomy of the prostate contours, thereby compensating for the poor tactile information provided by laparoscopy. The study's authors conclude that real-time TRUS significantly reduces the incidence of positive surgical margins. In the future, the use of real-time transrectal guidance will improve radical prostatectomy techniques.


